Pain management billing software with human-governed AI RCM

Pain Management Billing Software for End-to-End RCM

Connect procedure readiness to billing work without replacing your EHR.

Pain practices coordinate recurring procedures, payer-specific authorizations, levels and laterality, medical-necessity records, coding, and post-payment follow-up. QuickIntell brings that administrative work into one source-linked workflow, with review gates for clinical, coding, payer, and financial decisions.

  • Procedure scope

    Order, stage, level, side, and supporting records stay together.

  • Authorization

    Payer requirements, status, units, and effective dates remain visible.

  • Coding review

    Attested notes move to a human-reviewable coding worklist.

  • Payment follow-up

    Remittance exceptions, denials, and aging work reach named owners.

Healthcare professionals reviewing an administrative workflow on a laptop

One case record, explicit human checkpoints

Automation organizes evidence and work; qualified people retain coverage, clinical, coding, and release decisions.

Pain Management clinician and patient sharing a warm, attentive moment in a clinic

Connected module map

From insurance checks to payment follow-up

Configure only the parts your team needs. Each module can exchange case context with the next while exceptions and approval gates stay visible to the responsible staff member.

The pain-specific operating problem

Procedure detail can break between the order, authorization, and claim

A flat status cannot explain which procedure version was reviewed, which evidence was submitted, or which decision remains open. QuickIntell gives operations teams a shared administrative record without turning software into the clinician or payer.

The requested procedure is not one generic event

Epidural, facet, medial-branch, radiofrequency-ablation, neurostimulation, and peripheral-nerve requests can depend on stage, region, level, side, provider, site, and service date. The workflow keeps each version tied to its source instead of filling gaps from an old claim or schedule note.

Evidence arrives from more than one record

Signed notes, conservative-treatment history, imaging-report references, prior procedures, outside records, and payer instructions can disagree or arrive late. QuickIntell can organize what is present, missing, or conflicting; qualified staff still interpret clinical evidence and payer criteria.

Approval status is not the end of the workflow

Units, effective dates, response scope, procedure changes, claim edits, remittance reasons, and follow-up deadlines must stay connected to the exact request. Version history helps scheduling and billing teams avoid acting on an obsolete response.

Clinician and colleague reviewing a procedure workflow on a tablet
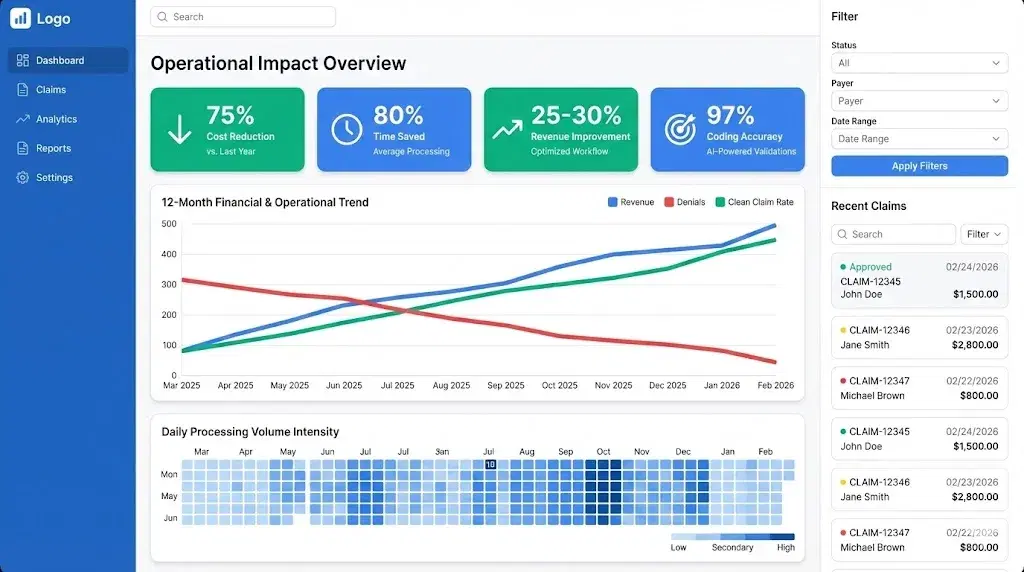
Operations team reviewing a revenue cycle dashboard

Human review and escalation

Automation that pauses at the decisions your team owns

QuickIntell can assemble context and move routine work, but it does not establish medical necessity, determine coverage, guarantee an authorization, or replace professional coding judgment. Your implementation defines where a person must review, approve, or take over.

Choose the automation mode per handoff

Start in an observe-only or notification mode, move to approval-gated execution, and automate a configured step only after your team validates it. High-stakes actions can remain approval-gated.

Keep clinical and coding authority with people

The AI Medical Scribe produces a draft for provider attestation. Medical Coding can suggest codes and surface edits, while authorized coders and clinicians review the source record and resolve questions.

Route uncertainty instead of hiding it

Missing evidence, conflicting procedure details, low-confidence matches, portal-only payer steps, and failed integrations become visible exceptions with an owner and next action.

Preserve the review trail

Case history can retain source links, status changes, approvals, overrides, and write-back events so teams can reconstruct what the software did and what a person decided.

Appointment to payment

An end-to-end pain management RCM workflow with visible handoffs

The workflow connects pre-visit checks, procedure-specific authorization, attested documentation, code review, claim release, remittance, and follow-up. Each stage retains its source, status, owner, and configured human checkpoint.

  1. 1

    Eligibility Verification

    Verify coverage

    Pull active coverage, benefit, and payer context for the planned date of service; route missing or inactive details for staff follow-up.

  2. 2

    Prior Authorization

    Build the procedure record

    Keep procedure family, stage, region, levels, side, history, source records, requirements, units, and effective dates on one versioned case.

  3. 3

    AI Medical Scribe

    Attest documentation

    Draft encounter documentation from the configured workflow, then require the provider to review and attest the final note.

  4. 4

    Medical Coding

    Review the code set

    Present supported code and modifier suggestions beside the attested source so a coder can accept, edit, or request clarification.

  5. 5

    Denial Prevention + Claims

    Check and release

    Surface configured authorization, payer-edit, documentation, and coding conflicts before an authorized person or rule releases the claim.

  6. 6

    Payment Posting

    Post the remittance

    Match configured ERA and EOB details, post clean lines, and send mismatches, reversals, or missing information to an exception queue.

  7. 7

    Denial Management + AR Management

    Resolve follow-up

    Keep payer reasons, source records, deadlines, aging, underpayment questions, and next actions connected to the responsible owner.

  8. 8

    Analytics + EHR Integration

    Measure and write back

    Review workflow trends and return only configured statuses, codes, and payment details to the system of record after the required gate.

Go deeper on pain procedure readiness

See how one focused workflow versions procedure identity, medical-necessity records, prior-procedure frequency, payer sources, packet review, and post-submission changes without making clinical or coverage decisions.

Explore the Procedure Workflow

Operational benefits

Give pain management RCM teams control over the work between systems

The value comes from connected context, explicit ownership, and reviewable automation. Results depend on workflow scope, source data, payer behavior, configuration, and staff adoption.

Pain Management clinician and patient sharing a warm, attentive moment in a clinic

One accountable case record

Keep the requested service, sources, payer response, changes, and downstream billing state connected instead of relying on a status copied across inboxes and spreadsheets.

Earlier exception visibility

Show missing records, conflicting procedure details, expired dates, failed connections, and unmatched remittance lines before they disappear into a later queue.

Clear ownership at each handoff

Assign clinical questions, authorization follow-up, coding clarification, claim edits, denials, and aging work to the appropriate role with a due state and history.

Operational evidence for improvement

Use source-linked drill-downs and workflow trends to find recurring handoff problems. Validate changes against real queues rather than relying on an assumed savings percentage.

Integrations and implementation

Connect to your EHR, then phase the rollout around real work

QuickIntell is designed to work alongside the system of record. Depending on vendor access and workflow scope, connections can use FHIR, REST APIs, configured adapters, browser automation, or file exchange. The implementation team confirms the available method and authorized fields before go-live.

Learn more about EHR Integration and configured write-back.

  1. 1

    Map the current workflow

    Document the trigger, source system, required fields, payer channel, existing handoffs, responsible role, and downstream destination for each in-scope step.

  2. 2

    Configure and test connections

    Validate field mappings, permissions, test transactions, exception paths, and permitted write-back against representative non-production or approved test cases.

  3. 3

    Start with approval gates

    Run selected handoffs in observe-only or approval-gated modes while staff compare the proposed action with the source record and payer-specific process.

  4. 4

    Expand after acceptance

    Move a validated handoff to its agreed mode, monitor exceptions and audit history, and keep a rollback path when a payer, form, interface, or clinic process changes.

Healthcare staff reviewing connected administrative work

Implementation output

An agreed data map, exception path, approval matrix, test record, role plan, and go-live checkpoint for each enabled handoff.

Trust and operational control

Security controls for PHI-bearing revenue cycle workflows

Security fit depends on your enabled modules, data flows, agreements, user roles, and implementation. QuickIntell provides controls for access, data protection, auditability, and governed write-back; your team validates the configuration for its policies and obligations.

Role-Based Access Control

Scope access and actions by organization and job responsibility so clinical, authorization, coding, billing, and administrative roles do not share one broad permission set.

Protected data handling

Use encryption in transit and at rest, organization-level data separation, credential protection, and signed access for supported file workflows.

Reviewable activity history

Retain audit events for status changes, approvals, overrides, sensitive actions, and configured automation so authorized reviewers can trace the workflow.

Controlled system write-back

Limit outbound fields and destinations, route sync conflicts for review, and keep clinical data from being silently overwritten when connected systems disagree.

Healthcare operations team discussing workflow controls

Practical RCM review guide

Pain-management billing: preserve site and treatment history

QuickIntell Editorial Team · Guide updated

A procedure name alone does not identify the complete administrative case. Keep anatomical detail, laterality, prior treatment records, the requested intervention, and the performed service linked without converting payer criteria into clinical conclusions.

  1. Review step 1

    Reconcile levels and sides

    Compare the scheduled intervention with the authenticated procedure note, anatomical levels, laterality, and documented guidance. Let the clinician resolve ambiguity before the coder reviews the correct service combination.

  2. Review step 2

    Keep historical evidence source-linked

    Index prior procedures, documented response, and conservative-treatment records by date and author. Do not manufacture missing treatment history or infer that a payer criterion is met because a document exists.

  3. Review step 3

    Review repeat-service scope

    Track the current payer-product policy, service period, prior utilization, and response limitations. Route uncertain frequency or repeat-procedure questions for qualified review rather than applying one payer's interval to every patient.

Measure your own pilot

Count incomplete level/laterality records, missing historical sources, and repeat-service questions unresolved at scheduling. Measure clarification time and the quality of the resolved record, not an assumed increase in procedure volume.

Inspect procedure evidence and frequency review

Source scope and review limits

CMS separates NCCI coding edits from medical review; passing an edit is not evidence that a treatment is covered.

These are editorial workflow recommendations, not clinical advice, claim-specific coding instructions, verified customer results, or an attestation by a credentialed reviewer. Validate current payer rules, licensed code references, and local approvals before use.

Discuss a specialty workflow pilot

CMS coding and coverage reference

Pain management billing guidelines: NCCI edits and Medicare coverage

In the CMS NCCI practitioner and ASC procedure-to-procedure table, version v323r0 (2026 Q4), 81 codes in the pain management ranges listed below are column one in 16,093 active pairs, and 71% of those pairs carry modifier indicator 1, so an NCCI-associated modifier can bypass the edit when the record supports a distinct service. The hospital outpatient table holds 13,846 pairs for the same codes. The 2026 Q4 practitioner Medically Unlikely Edit table sets a value for 81 codes in these ranges, all of them applied per date of service, and 64 of the values allow a single unit. 10 codes in the ranges are add-on codes that must be billed with a primary procedure. The most frequent edit rationale is “Misuse of Column Two code with Column One code” (6,144 pairs).

Code ranges counted: 20550-20553 (tendon, ligament and trigger point injections); 20600-20611 (arthrocentesis and joint injections); 27096 (sacroiliac joint injection); 62320-62327 (epidural and intrathecal injections); 63650-63688 (spinal neurostimulators); 64400-64530 (nerve blocks and transforaminal injections); 64490-64495 (facet joint injections); 64633-64640 (nerve destruction). The ranges are our selection of where pain management services sit in the code set, not a CMS classification.

What the 2026 NCCI Policy Manual says

Epidural injection codes 62321, 62323, 62325 and 62327 already include fluoroscopic or CT guidance, so 77003 or 77012 is not added. The physician performing a procedure does not report 62320-62327 or 64400-64530 as anesthesia for it, and local anesthetic for a musculoskeletal procedure is not billed as a trigger point or tendon sheath injection.

Most-bundled column-two codes inside these ranges

Each code is the column-two code in this many active practitioner pairs whose column-one code is also in the ranges. Open one in the NCCI checker to see its pairs and modifier indicators.

Sources: CMS Medicare NCCI Policy Manual (2026 edition) and the quarterly NCCI procedure-to-procedure, Medically Unlikely Edit and add-on code files, edit version v323r0 (2026 Q4) effective 2026-10-01; counts computed by QuickIntell from those files, see the methodology. CPT codes are shown as numbers only; CPT is a registered trademark of the American Medical Association. A summary for orientation, not billing or legal advice: check the CMS text and your Medicare Administrative Contractor before you code.

Pain management billing software FAQ

Questions from pain management RCM teams

Practical answers about EHR fit, procedure authorization, human review, integrations, denials, implementation, and security controls.

Is QuickIntell an EHR or practice-management replacement?

No. QuickIntell is revenue cycle and administrative workflow software that works alongside the existing system of record. Clinical teams can remain in their EHR while configured case context and approved results move through connected billing workflows.

What should a pain practice look for in billing software?

Evaluate whether the software can keep procedure identity, prior-authorization evidence, coding review, claim state, remittance, denials, and aging work connected. Also confirm the available EHR and payer connections, exception handling, human approval gates, audit history, role controls, implementation scope, and a clear fallback when automation cannot complete a step.

How does the workflow handle medical-necessity records and procedure frequency?

QuickIntell can assemble source-linked records and a procedure-aware history that distinguishes stage, region, level, side, service date, and event status. It can show what is present, missing, or conflicting, but qualified clinicians and authorized payer-policy staff decide what the evidence means and which events count under the controlling requirement.

Where do people review AI-assisted work?

Review points are configured by handoff. Providers attest drafted notes, coders review code suggestions, staff can approve authorization and claim actions, payment-posting exceptions route to a queue, and sensitive or low-confidence cases escalate to a named role. A workflow can remain observe-only or approval-gated instead of running automatically.

How does EHR and payer connectivity work?

The available connection depends on vendor access, the payer channel, and purchased scope. Implementations may use FHIR, REST APIs, configured adapters, browser automation, or file exchange. Field mappings, credentials, permissions, test transactions, failure handling, and any write-back are confirmed before go-live.

What happens after an authorization or claim denial?

The denial can become a tracked case with the payer reason, affected request or claim, source records, owner, deadline, and next action. QuickIntell may organize evidence or draft follow-up, but authorized staff review the record and choose the clinical, coding, contractual, or appeal response. No outcome is guaranteed.

What does implementation look like?

Implementation begins with workflow scope, source and destination mapping, access review, role design, representative test cases, exception paths, and user acceptance. Teams can phase from observe-only to approval-gated and then to an agreed automation mode after validating each handoff; high-stakes steps can remain human-gated.

What controls protect pain management billing data?

QuickIntell supports organization-scoped role access, encryption in transit and at rest, credential protection, signed access for supported file workflows, and audit events for sensitive actions. Security and compliance fit still depend on the configured data flow, agreements, access policies, and implementation review.


Plan the next step

Map your pain management billing workflow end to end

Bring a real administrative path. We will identify source data, system handoffs, exception owners, human checkpoints, and a phased implementation scope without assuming an authorization, payment, or savings outcome.

Pain Management Billing Software & AI RCM